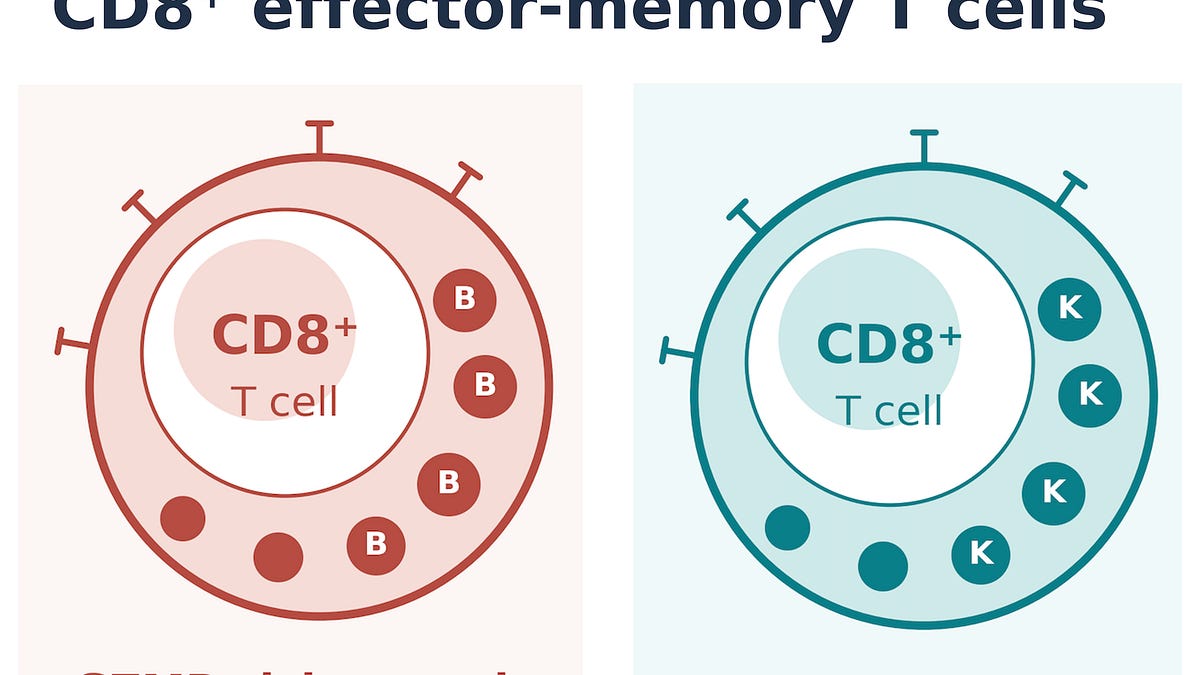
In the journal Immunity a paper with an obscure title was published on October 9th, 2026. It was entitled “Single-cell analyses of global cohorts outline determinants of immune aging and link the ratio of GZMK+ to GZMB+ Tem cells to health trajectories,” which I think is one of the worst titles I have ever seen for, ironically, one of the most important papers in the science of aging. I still don’t understand why authors and journal editors use or allow such arcane titles!
In this edition of Ground Truths I’m going to unpack the extraordinary work done by the team led by Maxim Artyomov. It takes our understanding of how our immune system ages—both healthily and unhealthily—to a new level with practical implications for determining its status, and promoting our healthspan.
This turns out to be a tale of two cells—different subtypes of memory T cells—that contain distinct types of granules resulting in divergent functions. And, importantly, major health outcomes.
Some very impressive stats for who was studied and what was done:
—8 international cohorts, 2,609 individuals, 12,394,834 white blood cells
—age 18 to 98 years
—59 immune cell types from sc-RNA seq harmonization
The story starts with the thymus gland, which starts to involute in early life and accelerates after puberty, after which there is progressive loss of naive T cells and recent thymic emigrants (RTEs) with ageThis decline was the strongest predictor of chronological age in the study. The problem is not so much that the naive T cells, the “rookies,” are declining but what is coming in, as the immune system adapts, to replace them—the “veterans.”
Until this study, prior cell sorting (flow cytometry) or pooled sequencing methods could not differentiate CD8+ effector memory T cells. That was only enabled by obtaining single-cell transcriptomes at scale.
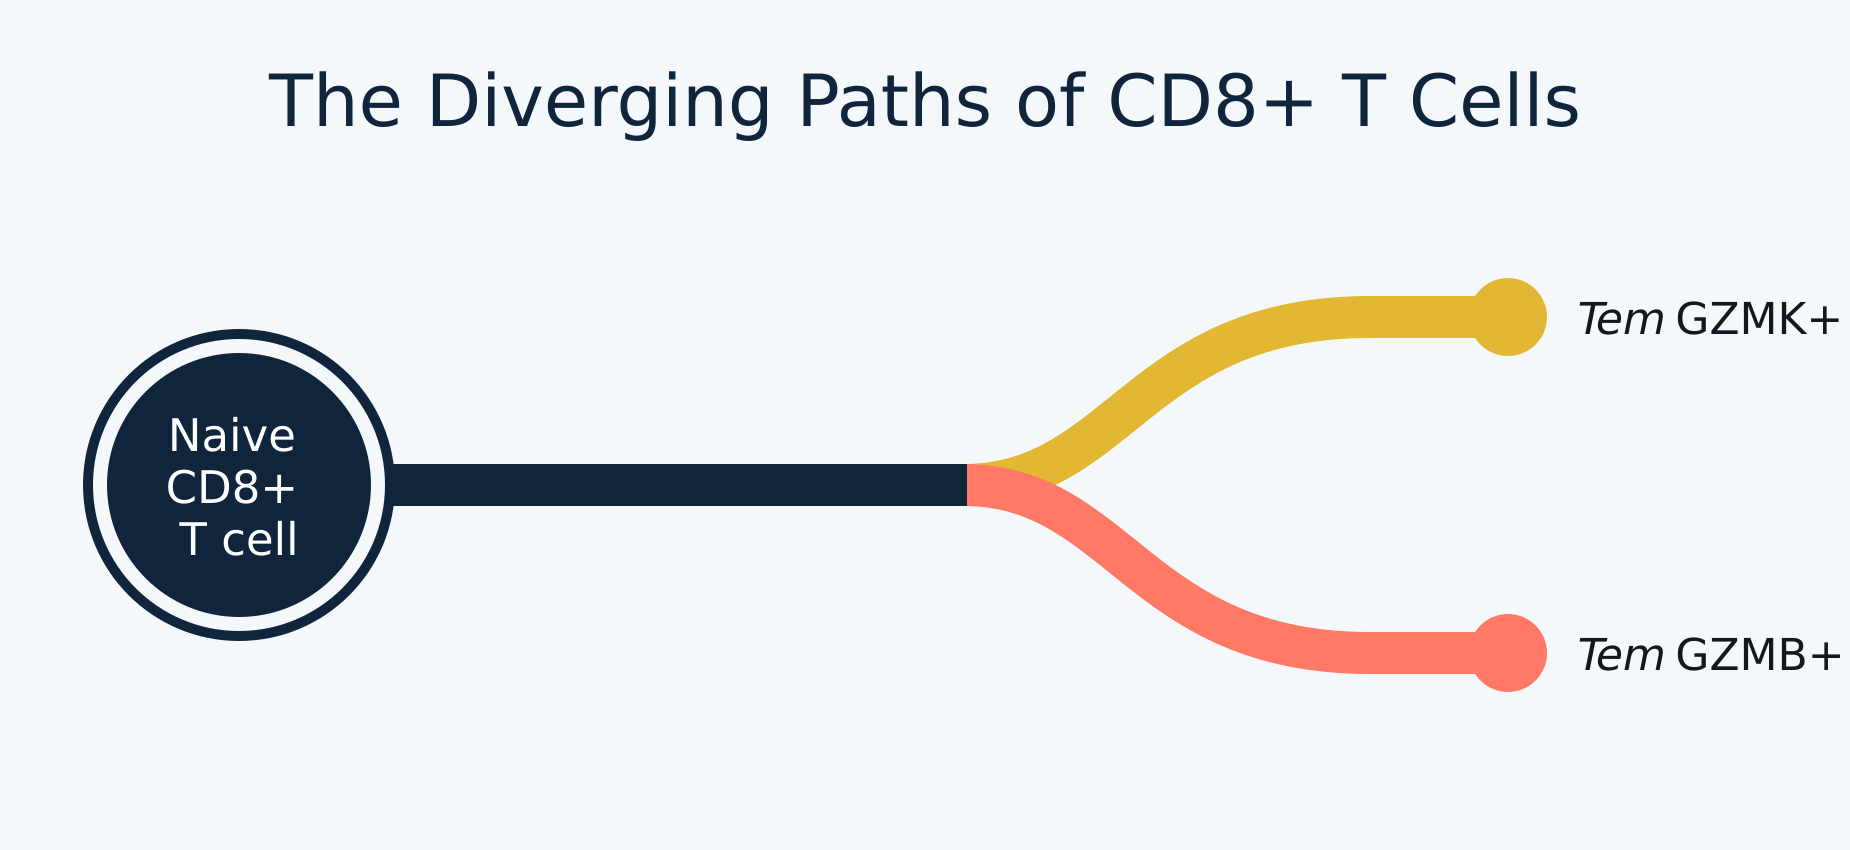
The 2 types of veterans are effector memory T cells (Tem) that are either mainly granzyme K or B. You can think of the B is “bad,” since these cells are leaky, exhausted, and spilling of their granules leads to dissolution of matrix, disruption of tissue, activation of macrophages, and inflammation. That profile of the terminally differentiated GZMB+ cells was characterized from experiments in mice. The bifurcation (Figure below) is influenced towards GZMB+ by cytomegalovirus (CMV) exposure and chronic diseases, such as cardiovascular (CVD) or metabolic (such as Type 2 diabetes).
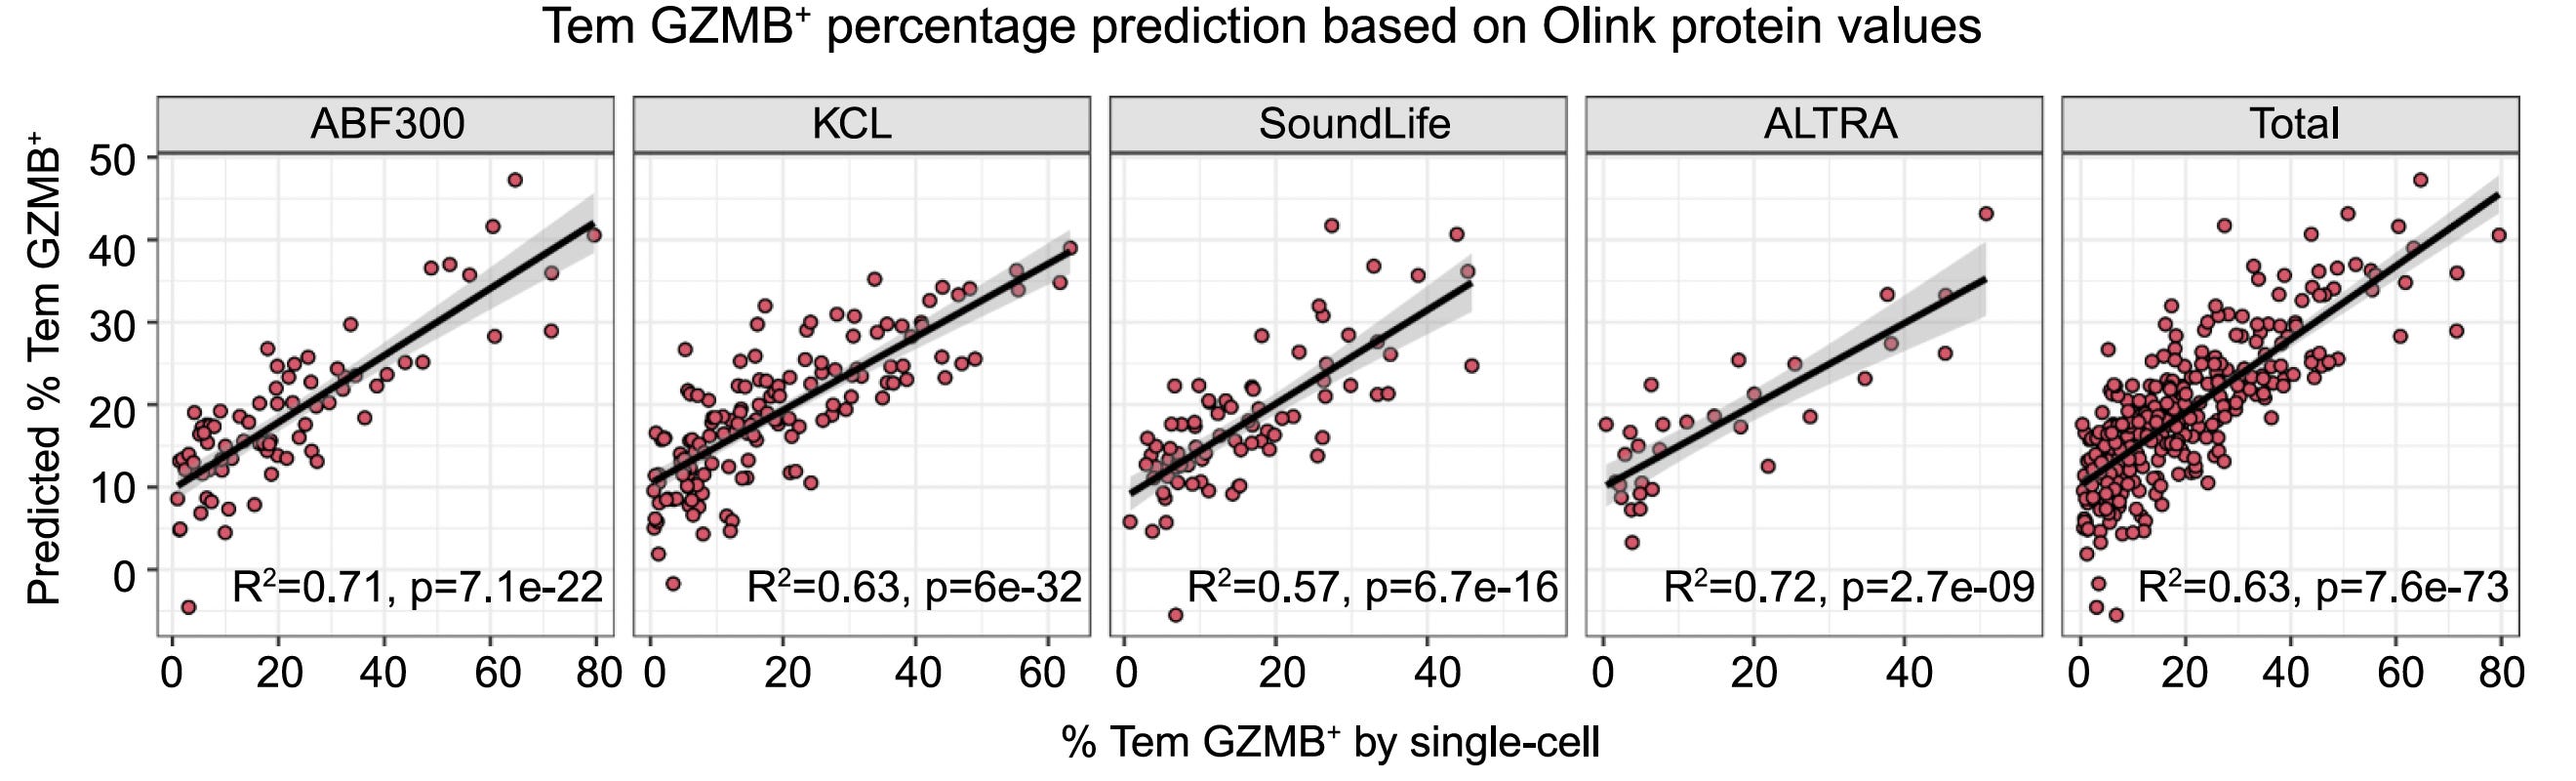
Doing single-cell RNA seq at scale to correlate with clinical outcomes or for development of a clinically useful blood test is not practical, not to mention expense. Instead, using the Olink assay of thousands of plasma proteins in 4 independent cohorts (of the 8 used in Phase 1) per cent TemB+ (Tem stands for T effector memory cell) correlated the best with the single cell GZMB+ data (using a LASSO computational model). That protein signature was tightly correlated with the single-cell RNA-seq work, as seen below in each of the 4 cohorts.
Note: Throughout this post please recognize the interchangeability of terms established between GZMB+ and TemB+, or GZMK” and TemK+.
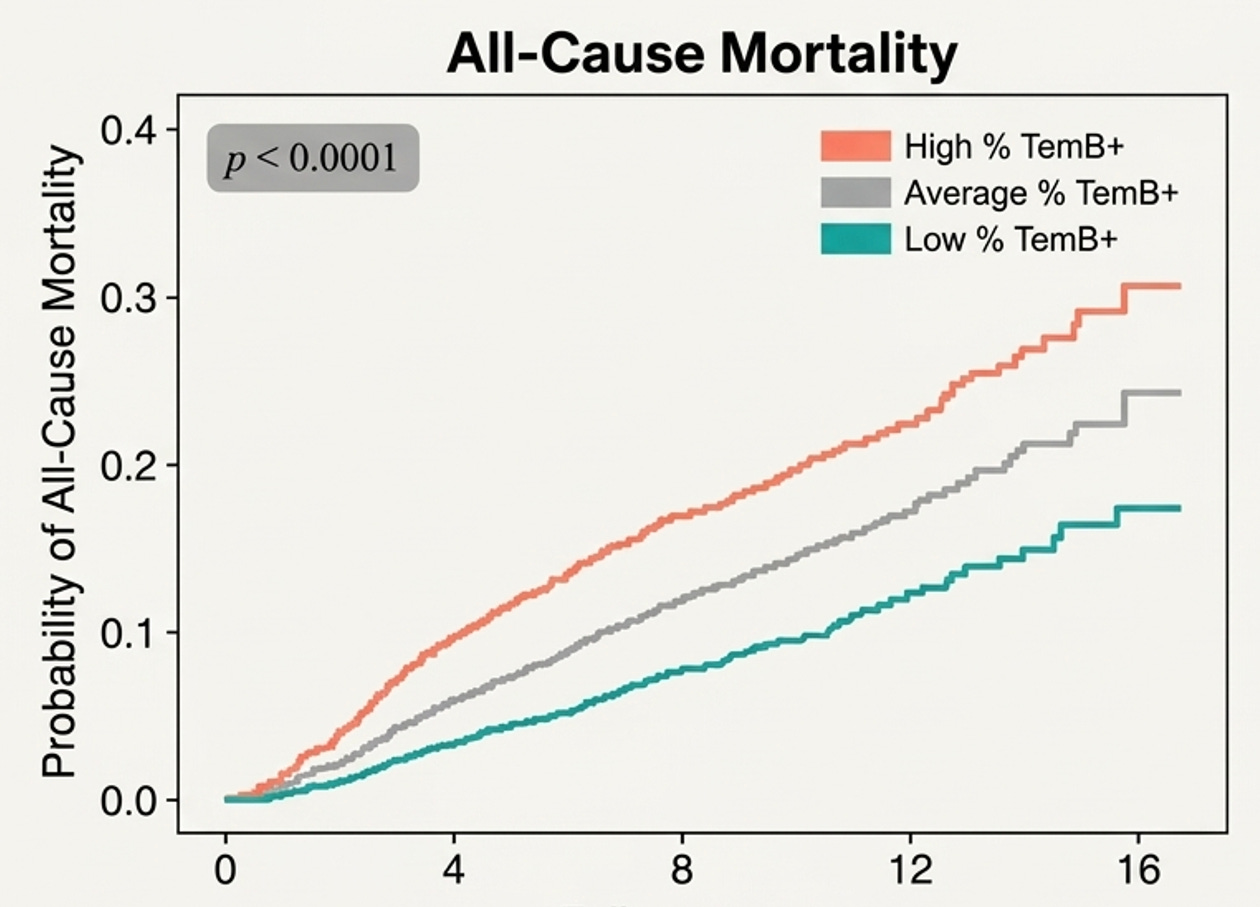
Then TemB+ was validated for clinical outcomes in the UK Biobank in 48,620 participants with 17-year follow-up, using both the cell protein data. As you can see below, individuals with a high per cent TemB+ had a much higher all-cause mortality than those with low % Tem B+ or the average group, as categorized in tertiles. The x-axis is years of follow-up.
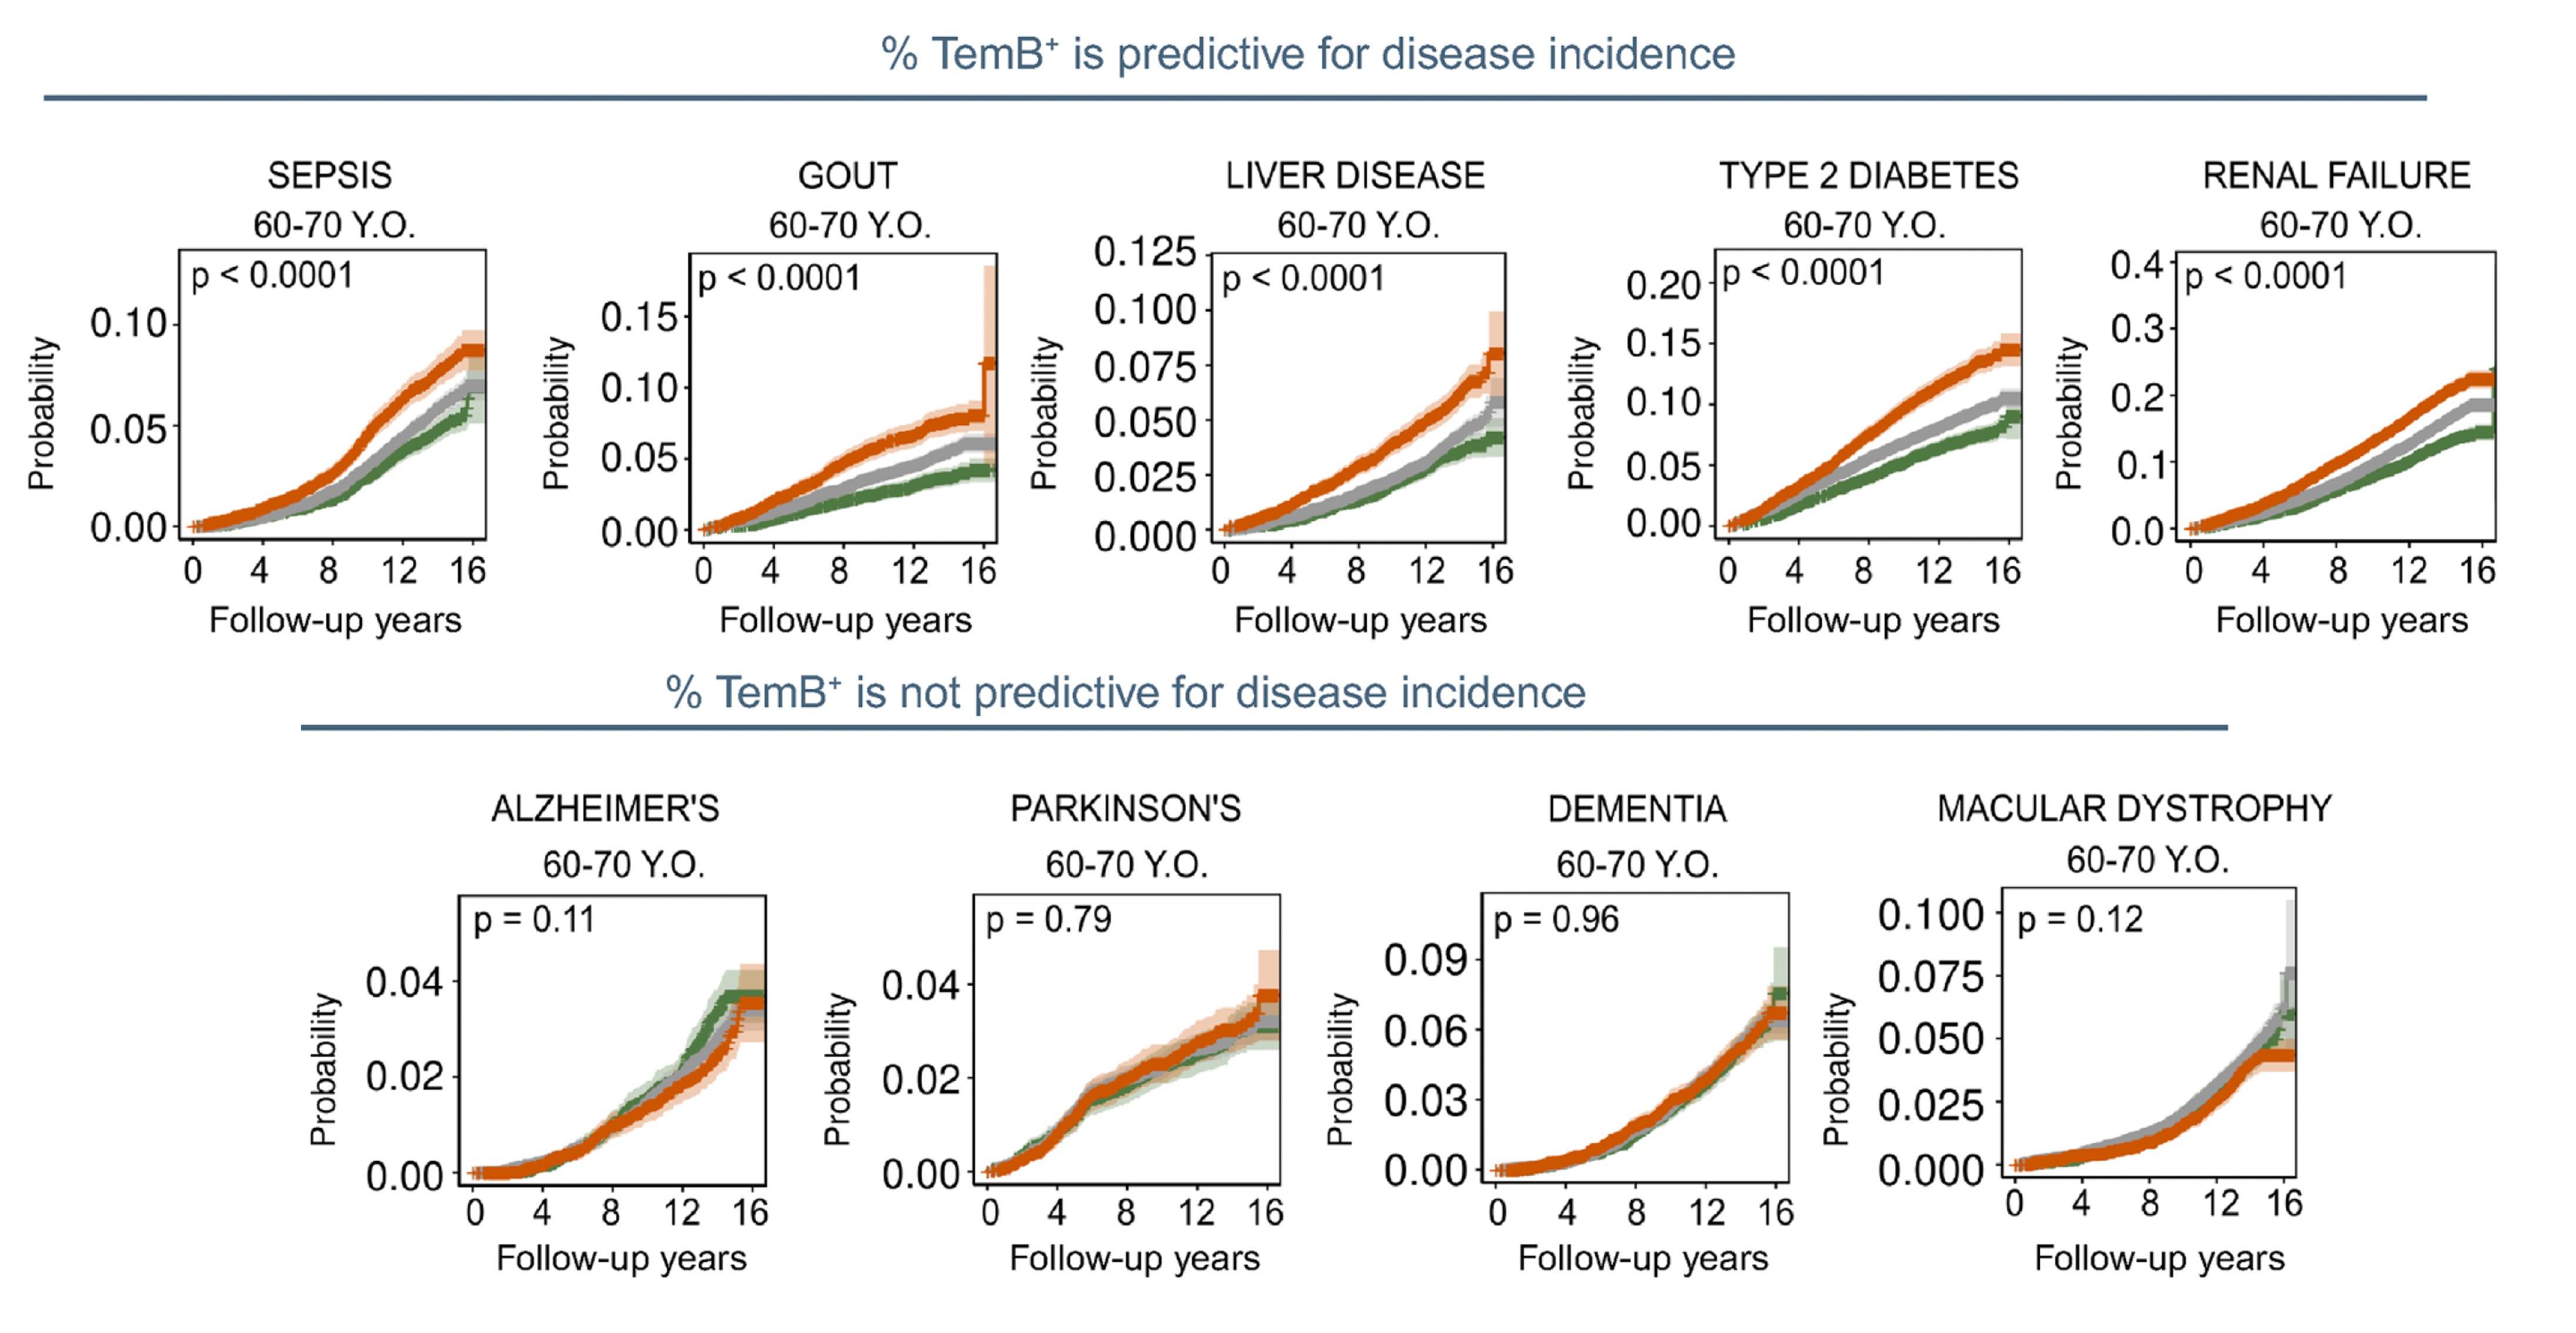
The TemB+ % was predictive of multiple specific health outcome as shown below.
In contrast, however, note the lack of any predictive correlation with neurodegenerative diseases and macular degeneration : Alzheimer’s disease, Parkinson’s disease, dementia, and age-related macular degeneration.
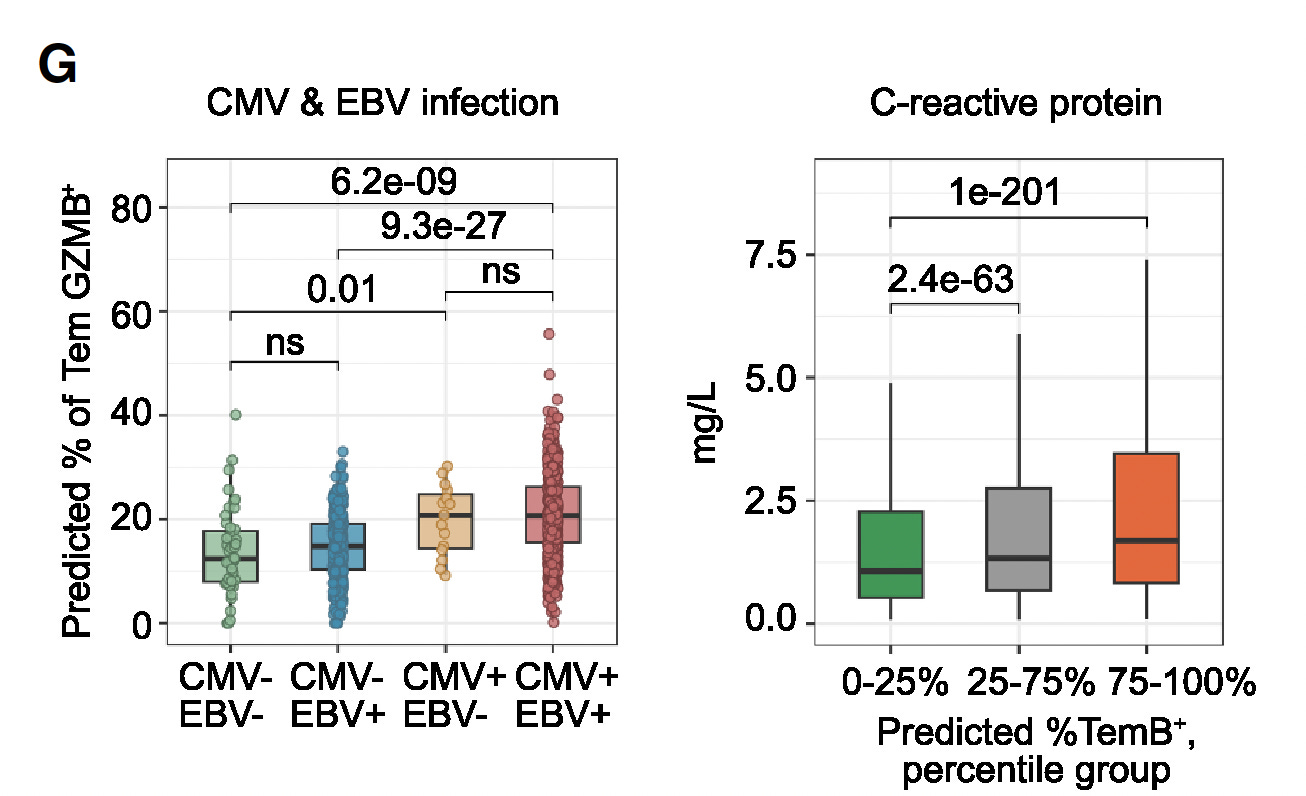
To emphasize the contribution of viral exposure and inflammation, the people who were seropositive for CMV had higher GZMB+ and those with higher C-reactive protein had higher % TemB+
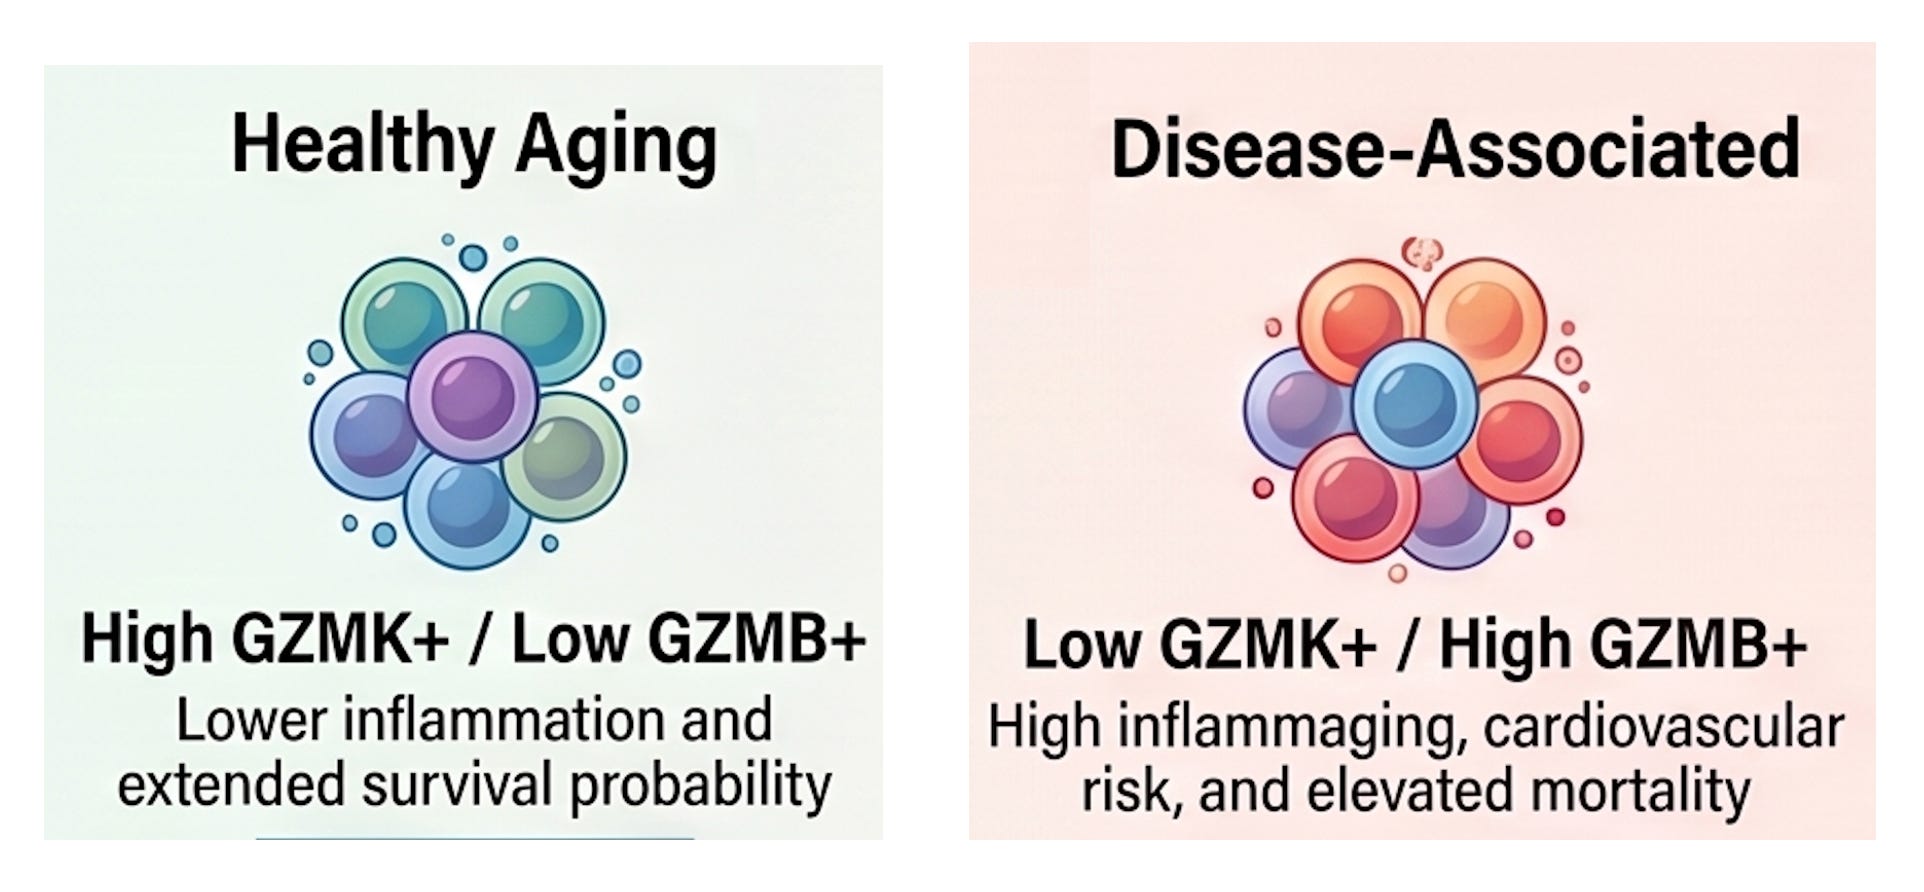
Here is a simplified dichotomy of clinical outcomes and inflammaging based on high Tem B+% (or GZMB+).
Of course there are plenty of limitations. The patients in the multiple cohorts were predominantly of European and Asian ancestry, leaving some uncertainty as to whether the findings will extrapolate to those of African ancestry. The window into immune cell aging was purely via blood cells, not tissue. “TemB+ was measured at a single time point, so we don’t know how it changes within a person, or whether lowering it changes the risk. Importantly, the dichotomy of the “good” and “bad” TemK+ and TemB+ cells, respectively, is an over-simplification, since we know K cell granules can also promote inflammation. CD*+ T cell counts weren’t available in the UK Biobank so they had to be imputed with a model. None of this work is establishing causality. I have not gotten into the “weeds” of the report, which is a beast to read and unravel, and there is much more about different types of cells, other mouse experimental data, Type 2 immunity remodeling, and so on.
This is a seminal paper, the most comprehensive assessment of white blood cells across the human lifespan that tracks immune cell aging and its relationship with survival and multiple adverse health outcomes. Let me break it down to the key points:
-
Primacy of the thymus gland. The study identified the decline in naive T cells and recent thymic emigrants as the basis of the aging clock, predicting chronological age.
-
It’s not just that we lose naive T cells as the thymus involutes, but it’s about the type of cells that come in to replace them. And it turns out there’s a critical bifurcation between TemK+ and TemB+ cells. The difference in the granules of these cells can account for inciting or fostering inflammation. Extensive characterization of the TemB+ cells from mice showed their propensity to be leaky, exhausted, and tissue disruptive.
-
Viral exposure, most notably by CMV blood positivity, affects the bifurcation path to promote TemB+ cells.. The other main influence on promoting TemB+ instead of TemK+ were chronic diseases, notably cardiovascular and metabolic.
-
The discovery in the work using single-cell RNA sequencing in >12 million white blood cells of the bifurcation and link to outcomes might not have been made with traditional methodologies of cell sorting, flow cytometry, or pooled sequencing. This is yet another reinforcement of getting “granular” (no pun intended with granules) with respect to learning from single-cell data.
-
A new protein blood test emerges from this body of work, the percent of TemB+, or ratio of TemB+ to TemK+. It might be considered a master indicator of unfavorable immune system aging. This could lead to a simple and inexpensive window into a person’s immune status and the researchers in the current study are indeed pursuing that goal. For people found to have an unfavorable immune status, we know of ways that can be improved with lifestyle factors and vaccines, and much more will be done in the years ahead to find other means.
-
Here in late 2026 we have no way of assessing a person’s immune system in the clinic, as I’ve previously written on “Why We Need an Immunome.” Ironically, we have so many ways to control the immune system, releasing its brakes (think immune checkpoint inhibitors and ten other classes of interventions) and B-cell depletion or “inverse” vaccines to induce tolerance in autoimmune conditions. We can dial it up or down but can’t measure it!
In recent months we have seen 2 new practical ways to get at this crucial assessment: (1) AI analysis the thymus gland from a low resolution chest CT (See “Your Thymus and Your Healthspan”) and (2) Proteomic clocks of the immune system and immune cells (see “Medicine is Moving from Calendars to Clocks”) from a blood test. Both these immune system assessments are now moving towards commercial availability. The current study represents a 3rd path. In short, we’re getting there!
NB. I wrote this post. I did use AI to generate four of the Figures as noted above to help the reader visualize what I was writing about. I have no conflicts of interest related to this topic or post.
Ground Truths has 217,000 subscribers from every US state and 214 countries. There are over 320,000 followers of Ground Truths so more than 100,000 folks who can easily convert to be free subscribers. If you’re one of them, please consider doing so.
Your subscription to these free essays and podcasts makes my work in putting them together worthwhile. If you’re not a subscriber, please join!
If you found this interesting PLEASE share it!
The proceeds from all voluntary paid subscriptions go to support our summer internship program. It enabled us to accept and support a record number of 62 summer interns that joined us in 2026! These are high school, college and medical students selected from thousands of applicants. We couldn’t do this expanded program without the funds coming in through Ground Truths. Thank you!