
Those differences may offer clues to why the disease can sometimes behave more aggressively at a younger age. Researchers from Massachusetts General Hospital, Brigham and Women’s Hospital, Dana-Farber Cancer Institute and the Broad Institute of MIT and Harvard mapped gene activity in more than 850,000 cells from 189 tumors.

According to the American Cancer Society, colorectal cancer incidence among Americans under 50 increased by 2.9% each year between 2013 and 2022. The disease is now the leading cause of cancer death in this age group in the United States. At the same time, overall incidence and mortality have declined in recent decades, partly because of screening and improved treatment. The decline between 2013 and 2022 was driven mainly by falling rates among people 65 and older, while incidence rose modestly among those aged 50 to 64. Against the backdrop of rising cases in younger adults, the recommended starting age for routine screening in average-risk Americans was lowered from 50 to 45.
Younger people also tend to be diagnosed at a more advanced stage. According to the American Cancer Society, about three in four colorectal cancer cases among Americans under 50 are detected after the disease has spread locally or to distant organs. Distant metastases are found at diagnosis in about 27% of younger patients, compared with 21% to 23% in older age groups.
“We are seeing far more young people with cancer than we used to,” said Dr. Yaron Rudnitzky, director of the Colorectal Surgery and Proctology Unit and deputy director of the Surgical Division at Meir Medical Center, part of Clalit Health Services. Most of the younger patients he sees are around 40, he said, although some are even younger.
“People in their 40s don’t think they can have cancer,” he said. “Very often they have been walking around for a year with abdominal pain, bloody stools or weight loss. By the time they are diagnosed, they often arrive with more advanced disease.”
Rudnitzky pointed to two factors that may contribute to delayed diagnosis. “We don’t have a routine screening protocol for young people,” he said. And even after symptoms appear, cancer is not always immediately suspected.
The question is whether the later stage at diagnosis also reflects the biology of the tumors themselves.
“The big question in the field has been, ‘Why is this increasing?’ and the second question is, ‘Is this a different disease?’” said Prof. Ana Anderson, director of the Cancer Program at the Gene Lay Institute of Immunology and Inflammation at Brigham and Women’s Hospital and one of the study’s senior investigators.
 Dr. Yaron RudnitzkyPhoto: Rami Zarnegar
The study, the largest of its kind, analyzed tumor samples removed during surgery at Brigham and Women’s Hospital and preserved frozen in Dana-Farber’s tissue bank. The samples came from patients ranging in age from 29 to over 90. Fifty-four had been diagnosed before age 50, while 135 were diagnosed at 50 or older.
Researchers used a technique known as single-nucleus RNA sequencing, which allows scientists to determine which genes are active in individual cells. Because the method can be used on frozen tissue, the team was able to analyze archived samples accompanied by extensive medical information. In all, they mapped gene activity in more than 850,000 cells, including cancer cells and other cell types found within tumors.
In some statistical analyses, the researchers treated age as a continuum rather than simply comparing patients under and over 50, looking for biological characteristics that changed gradually with age. They also accounted for tumor location, disease stage, sex and treatment received before surgery. That allowed them to identify patterns that a simple two-group comparison might have missed.
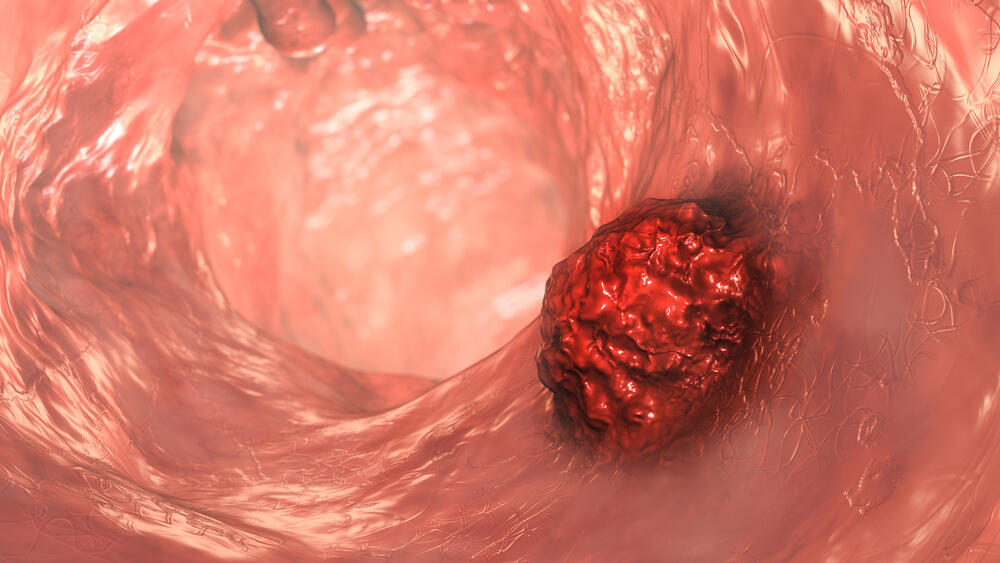
Colorectal cancer
(Photo: shutterstock)
“When we looked beyond conventional age cutoffs, we uncovered biological patterns that previous studies may have missed,” Anderson said.
The most striking finding involved the tumors’ cellular composition. In microsatellite-stable, or MSS, colorectal cancer, the most common subtype of the disease, tumors from younger patients had a higher proportion of stromal cells relative to cancer cells.
Stromal cells are connective and supporting cells that form a kind of framework around and between cancer cells. They can influence tumor growth and, under certain conditions, may make it harder for immune cells and drugs to reach and attack cancer cells. In several types of solid tumors, a high proportion of stromal tissue has been associated with resistance to chemotherapy.
The same pattern appeared in two additional groups analyzed by the researchers. One included gene-activity data from hundreds of tumors, while another used machine learning to analyze stained tissue images from 712 tumors.
“This could be an explanation for why younger patients may respond less well to treatment,” said Prof. Kimmie Ng, director of Dana-Farber’s Young-Onset Colorectal Cancer Center and one of the study’s senior investigators.
Within cancer cells from MSS tumors, researchers identified 215 genes whose expression was higher in younger patients and 44 that were more active in older patients.
A substantial share of the genes more active in younger patients produce long noncoding RNA molecules. Unlike conventional RNA that carries instructions for making proteins, these molecules do not encode proteins, although some can regulate the activity of other genes. Across the three major cancer-cell types analyzed, long noncoding RNAs accounted for roughly 30% to 45% of genes showing increased expression in younger tumors, with some appearing across more than one cancer-cell type.
About half of the long noncoding RNA molecules identified in this analysis belong to a poorly understood group sometimes described as “dark RNA.” Researchers still know relatively little about what they do.
Around 60% to 70% of long noncoding RNA is located inside the cell nucleus, according to the researchers. Because the study specifically analyzed nuclei, the method may have been particularly well suited to detecting differences that earlier colorectal cancer studies missed.
Much of the increase in colorectal cancer among younger adults has been linked to tumors in the distal, or left, side of the colon and in the rectum. In a computerized analysis focusing on left-sided MSS tumors, researchers identified 29 signaling pathways in which predicted communication between cells was stronger in younger patients’ tumors, compared with seven that were stronger in older patients.
Some of those pathways are associated with the ability of cancer cells to change their characteristics and invade surrounding tissue, while others are involved in forming blood vessels that supply the tumor.
To determine whether the differences might simply reflect the natural aging of the intestine, researchers compared their findings with data from normal intestinal tissue. Only five genes overlapped. The limited overlap, they said, supports the idea that the gene-expression patterns they identified are linked to tumor biology rather than normal aging.
“The study doesn’t tell us why this is happening in younger people,” Rudnitzky said.
When someone develops colorectal cancer at a young age, one of the possibilities doctors examine is hereditary predisposition. But in many of the younger patients he treats, genetic testing identifies no known inherited cause.
“We’ve constantly been looking for the holy grail, what characterizes these tumors in young people,” he said, adding that the findings reinforce his impression that the biology of tumors in younger patients may sometimes be more aggressive.
In his clinic, he sees young patients who already have metastatic disease at diagnosis or complications such as intestinal obstruction. For him, the newly identified molecular characteristics offer another direction for investigating whether tumor biology itself contributes to those outcomes.
The researchers stressed that their findings generate hypotheses about disease progression and treatment response but do not yet prove them. The sequencing method also recovered relatively few immune cells, leaving open the question of whether immune responses inside tumors also vary by age.
Prof. Heinz-Josef Lenz, a colorectal cancer researcher at the University of Southern California who was not involved in the study, described the findings as promising but cautioned that researchers still do not know whether the identified differences actually make tumors more aggressive or more resistant to treatment.
“That is the missing question,” he said.
Genetics is not the only factor being investigated in young-onset colorectal cancer
(Photo: shutterstock)
Prof. Ramnik Xavier, a gastroenterologist at Massachusetts General Hospital and another senior investigator on the study, said the research creates a foundation for examining how the cellular patterns interact with substances derived from diet and the gut microbiome, and whether those interactions contribute to the development of colorectal cancer at a younger age.
Ng said younger patients are currently generally treated in much the same way as older patients. Previous research in other cancers has already examined therapies aimed at stromal cells.
“Our hope is that with further research, these findings could perhaps eventually become targets for personalized treatment for our younger patients,” she said. “There is still a lot of work to do, but in recent years we have gained more insight than ever before.”
That progress, she added, gives patients hope that doctors may eventually understand their disease more precisely.
Under Israel’s national screening program, average-risk adults aged 50 to 74 are advised to undergo a fecal occult blood test once a year. In practice, Rudnitzky said, health funds also invite patients from age 50 to undergo colonoscopy as a screening test.
“It is important to emphasize that we are talking about healthy people without complaints or symptoms suggesting disease,” he said.
During colonoscopy, doctors can identify and remove polyps before some of them become cancerous. But when symptoms raise concern about colorectal cancer, medical evaluation is warranted at any age.
“In the United States, the recommended age was lowered to 45 because of recognition of the substantial burden of colorectal cancer before age 50,” Rudnitzky said. He believes Israel should consider whether to lower its screening age as well.
He recalled one 48-year-old patient who had experienced bleeding for two years before eventually being referred for a colonoscopy. Blood in the stool can result from hemorrhoids, he noted, and abdominal pain has many possible causes. But recurrent bleeding, persistent abdominal pain or unexplained weight loss should prompt a medical evaluation.
That is why early detection remains so important.
“It often makes it possible to undergo surgery to remove the diseased section of bowel, restore bowel function and achieve a complete cure in most cases,” Rudnitzky said. “Today, robotic surgery allows us to perform these operations with minimal morbidity and a faster return to normal life. That is especially important for younger patients, many of whom are at the height of their lives, with young children, relationships and developing careers.”
Meanwhile, at Meir Medical Center’s surgical division, researchers are returning to an even earlier point in the patient journey: the first visit to a doctor.
“We are conducting research on exactly this issue across Clalit,” Rudnitzky said. The team is examining the increase in colorectal cancer among younger people diagnosed over the past decade and whether the time between a patient’s first medical visit and the eventual diagnosis is linked to the stage at which the cancer is detected and to treatment outcomes.
“How long do they really wait from the moment they first go to the doctor and say, ‘My stomach hurts’?”